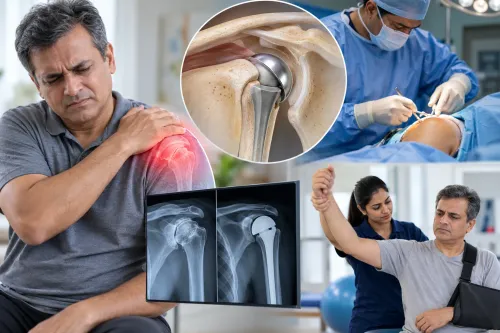
A shoulder that hurts when you move it is not automatically a frozen shoulder: a rotator cuff tear, fracture, dislocation, arthritis, nerve problem, or tendon irritation can produce a similar complaint. You will learn how to recognise the movement pattern that points toward adhesive capsulitis, which warning signs need prompt assessment, and when treatment may need to progress beyond home exercises.
Key takeaways
- Restricted active and passive movement suggests adhesive capsulitis.
- External rotation loss is a key frozen shoulder examination finding.
- Gentle exercises help; forceful stretching can worsen shoulder pain.
- Seek assessment when stiffness persists, disrupts sleep, or blocks daily tasks.
Does the movement pattern point to frozen shoulder or another problem?
The key distinction is active versus passive range of motion. In adhesive capsulitis, both the movement you perform yourself and the movement an examiner performs are restricted; this frozen shoulder movement pattern usually limits external rotation first and most severely.
| Pattern | What it may suggest |
|---|---|
| Unable to lift the arm actively, but near-normal passive movement | Weakness from a rotator cuff tear rather than a frozen joint |
| Overhead pain with preserved passive movement | Tendonitis or shoulder impingement |
| Grinding with persistent stiffness and restricted movement | Arthritis |
| Sudden deformity or the arm held out of position | Dislocation |
| Neck pain with tingling, numbness, or weakness | Nerve-related pain |
A fracture can also cause sudden pain and loss of movement, particularly after a fall, direct blow, or forceful movement. Treat that combination as a possible fracture or dislocation until a clinician assesses you.
A shoulder that remains stiff after a fracture, dislocation, tendon repair, or prolonged sling use is not automatically frozen shoulder. Healing bone, surgical hardware, tendon protection, or joint instability can change what exercises are safe.
Seek prompt medical assessment after new trauma, visible deformity, rapidly worsening pain, fever, or a hot, red, swollen joint. Do not force stretching while the diagnosis is uncertain.
How do the freezing, frozen, and thawing phases change the decision?
The phase changes what treatment can realistically achieve: the freezing phase is painful, the frozen phase is stiff, and the thawing phase restores movement gradually. These phases overlap, so symptoms do not always follow a clean timetable.
During the freezing phase, pain can dominate while movement steadily narrows. Use gentle, tolerable mobility and avoid forceful stretching, which can provoke guarding and a prolonged flare.
During the frozen phase, pain may settle even though marked stiffness remains. Reaching behind your back, lifting your arm, and rotating it outward are common trouble spots; regular mobility work and supervised therapy focus on preserving or recovering this range.
During the thawing phase, movement returns gradually rather than suddenly. The full course can last one to three years, so persistent stiffness alone does not prove that treatment has failed.
Seek prompt medical assessment for these shoulder stiffness warning signs:
- Sudden loss of movement after an injury
- Visible deformity
- Fever or a hot, swollen joint
- Rapidly worsening pain
- Unexplained weight loss
- Chest pain or shortness of breath
- New arm weakness or numbness
These symptoms do not fit an ordinary phase pattern. Do not stretch at home while waiting for an assessment, particularly after trauma or when weakness, numbness, fever, or severe pain is present.
What does an examination and scan need to rule out?
Frozen shoulder diagnosis is primarily clinical: both active and passive movement are restricted, rather than an imaging test confirming capsular inflammation. An appointment should map the movement pattern and test competing causes.
- Compare movement you perform yourself with movement the clinician performs.
- Measure external rotation and overhead reach; external rotation is commonly limited first.
- Test shoulder strength and look for signs of a rotator cuff tear or instability.
- Examine your neck and check sensation and reflexes if pain, tingling, or weakness suggests nerve involvement.
A plain shoulder X-ray can exclude glenohumeral arthritis, fracture, dislocation, and other bony changes. It does not confirm frozen shoulder by itself. A shoulder ultrasound assesses rotator cuff tendons and fluid around them, while a shoulder MRI evaluates the rotator cuff, labrum, cartilage, bone, and other soft tissues when another diagnosis is suspected.
Tell the clinician about diabetes, thyroid disease, previous shoulder injury or surgery, prolonged sling use, and other systemic conditions. These factors affect risk, tissue recovery, and treatment planning.
A stiff shoulder after fracture repair, tendon surgery, or immobilisation needs a plan that respects fracture healing, hardware, tendon protection, or joint stability. Labelling it frozen shoulder too quickly can lead to stretching or treatment that disrupts recovery.
What can you do safely before considering an invasive treatment?
Start with movement, not complete rest, but confirm the diagnosis first. A stiff shoulder after a fracture, dislocation, tendon repair, or prolonged sling use needs advice that protects healing bone, hardware, repaired tendons, or joint stability.
1. Use structured frozen shoulder exercises every day, guided by a clinician or physiotherapist when possible. Gentle stretching should produce a tolerable stretch or mild discomfort that settles; stop if you get sharp pain, guarding, or a substantial flare lasting into the next day.
2. Reduce exercise intensity during the painful freezing phase and avoid aggressive stretching. Keeping the arm completely still prolongs loss of movement, while forcing it through severe pain can increase irritation and make the shoulder harder to use.
3. Combine mobility work with paracetamol or an anti-inflammatory medicine when medically suitable. Pain relief should help you move; relying on painkillers without addressing restricted movement or an unconfirmed diagnosis will not correct the underlying problem.
4. A corticosteroid injection into the glenohumeral joint can improve early pain and function for the short term, especially alongside a mobility programme. If you have diabetes, discuss blood-glucose monitoring because the injection can temporarily raise glucose.
Hydrodilatation may improve pain and motion briefly, but it is not uniformly better than injection plus exercise and can itself be painful.
When might frozen shoulder treatment need a procedure or surgery?
Escalation is reasonable when passive shoulder movement remains substantially restricted, pain and daily function remain poor, and a well-supervised trial of exercise, suitable medication, and an appropriate injection has not helped enough. There is no fixed symptom duration that makes frozen shoulder surgery mandatory; many shoulders improve without an operation.
A specialist should confirm that the movement pattern is truly frozen shoulder and review imaging for arthritis, fracture, rotator-cuff injury, or another cause. The decision should also account for your work and daily limitations, diabetes or thyroid disease, bone and tissue strength, anaesthesia risk, and your ability to complete rehabilitation.
1. Manipulation under anaesthesia moves the shoulder forcefully while you are unconscious and can restore motion. It can also cause fracture, dislocation, rotator-cuff injury, or nerve injury, so caution is essential with osteoporosis, a previous fracture, significant diabetes, or weakened tissue.
2. Arthroscopic capsular release uses keyhole instruments to divide tight capsule tissue and can improve motion in treatment-resistant cases. It remains surgery, with risks of infection, bleeding, nerve or blood-vessel injury, recurrent stiffness, and further rehabilitation.
Both procedures require supervised exercises afterward to preserve the movement gained, and neither guarantees a permanent cure. An orthopaedic shoulder assessment with Dr Gaurav Gupta can match confirmed movement loss, scan findings, medical conditions, functional limits, and procedural risks to the next step.
Related service
Frozen Shoulder Treatment Frozen shoulder, medically known as Adhesive Capsulitis, causes pain, stiffness, and restricted shoulder movement. Dr. View service → |
Frequently asked questions
Does the movement pattern point to frozen shoulder or another problem?
Frozen shoulder restricts both active movement and passive movement, with external rotation usually limited first and most severely. If passive movement is preserved, consider problems such as rotator cuff pain or weakness instead.
How do the freezing, frozen, and thawing phases change the decision?
Pain and worsening stiffness dominate the freezing phase, marked stiffness with less pain defines the frozen phase, and movement gradually returns during thawing. The phase helps set expectations and guide treatment intensity.
What does an examination and scan need to rule out?
An examination checks active and passive range of motion, strength, neck-related symptoms, and signs of arthritis or tendon injury. X-rays can identify arthritis or fracture; ultrasound or MRI can assess the rotator cuff when weakness or another structural problem is suspected.
What can you do safely before considering an invasive treatment?
Keep the shoulder moving within a tolerable range, use prescribed stretching or physiotherapy, and manage pain as advised by a clinician. Avoid forceful stretching, heavy lifting, and exercises that cause lasting pain.
When might frozen shoulder treatment need a procedure or surgery?
A clinician may discuss a corticosteroid injection when pain blocks rehabilitation or daily activities. Manipulation under anaesthesia or arthroscopic capsular release is reserved for persistent severe stiffness after appropriate non-surgical treatment.